Adding platelet-rich plasma (PRP) to a clinical practice is an operational and regulatory project, not simply a new service on the menu. The decision touches four areas at once: FDA device status and off-label framing, equipment selection, clinician training, and the financial model. This guide walks through each area in a way that helps you plan an integration that is clinically sound, regulatory-defensible, and financially realistic.
In short: PRP preparation systems are FDA 510(k)-cleared for bone graft handling, so most clinical injection uses are off-label and overwhelmingly cash-pay. A defensible integration plan covers four pillars: regulatory and scope-of-practice alignment, the right equipment (centrifuge, FDA-cleared kits, ultrasound), clinician training with hands-on practice, and a realistic financial model that accounts for labor, marketing, and malpractice costs the vendor brochures leave out. Published per-session pricing ranges roughly from $350 to $2,815, with strong regional variation. Individual clinical and financial results vary.
Important Disclaimer
Regenerative Medicine Academy (RMA) is an education company providing training for licensed clinicians. This article is educational content only and does not constitute medical, legal, business, tax, or financial advice, nor a guarantee of clinical or financial outcomes. Platelet-rich plasma preparation systems are FDA 510(k)-cleared as Class II devices for bone graft handling; most clinical injection uses discussed here are considered off-label and subject to state and federal regulation. Clinicians are responsible for verifying FDA device status, state scope-of-practice requirements, informed consent obligations, malpractice coverage, corporate-practice-of-medicine rules, and applicable advertising laws (FDA, FTC, and state) before integrating any new service. Revenue and ROI figures are illustrative ranges from published sources, not projections for any specific practice. Individual clinical and financial results vary. Consult qualified legal, compliance, and tax professionals before acting.
Every week, a clinician somewhere decides to add PRP to their practice. Some do it well. They take their time, choose the right equipment for their indication mix, get real hands-on training, build a cash-pay workflow that actually collects, and write informed consent language that holds up to scrutiny. Others rush the launch and quietly lose money, or worse, inherit a compliance problem that follows them for years.
The difference is rarely clinical talent. It is planning. PRP integrations fail for predictable reasons: the wrong kit for the wrong indication, thin training, marketing language that invites regulatory attention, or a financial model copied from a vendor brochure that never survives contact with real overhead.
This guide lays out what a careful, defensible PRP integration looks like across regulatory framing, equipment, training, workflow, and financials. It draws on published market data, FDA device records, and peer-reviewed literature, and it flags where industry-published numbers deserve healthy skepticism.
The regulatory foundation: what clinicians should understand before buying anything
Before any equipment quote, spend time on the regulatory picture. PRP preparation systems are cleared under the FDA 510(k) pathway as Class II medical devices for intraoperative use with autologous bone graft material. That clearance covers how the device processes blood to improve bone graft handling properties. It does not approve PRP for any specific injection use in patients.
This means almost every common clinical use of PRP, including knee osteoarthritis, tendinopathy, hair loss, aesthetic applications, wound care, and sexual health indications, is considered off-label. Off-label use is legal when it reflects sound clinical judgment, but marketing language cannot state or imply FDA approval for these uses. A line like “FDA-approved PRP for knee pain” is both inaccurate and a predictable trigger for regulatory attention.
Reimbursement reality flows directly from this status. Medicare coverage of PRP is limited to one wound-care indication under a national coverage determination, and commercial payers generally classify PRP as investigational and do not cover it for musculoskeletal or aesthetic uses. A few exceptions exist in specific programs and indications, but they do not change the big picture. PRP is overwhelmingly a cash-pay service line, which shapes everything from consent language to billing infrastructure.
Scope of practice is the other piece of the regulatory foundation. There is no federal PRP certification mandate. State medical boards decide who may perform PRP injections and under what supervision. Physicians generally have the broadest authority. Nurse practitioners operate under full, reduced, or restricted practice authority depending on the state. Physician assistants work under delegation agreements shaped by the supervising physician’s scope. Registered nurses typically require standing orders or protocol authorization to perform injections. Some states also regulate aesthetic procedures under separate cosmetic rules that sit on top of the medical-practice rules. Before launching, verify your state board’s current position and confirm with your malpractice carrier that PRP is covered under your existing policy or requires a rider. The FDA’s patient and consumer information on regenerative medicine therapies provides useful context for the public-facing off-label conversation you will need to have with patients.
What this means in practice: regulatory due diligence is the cheapest investment in a PRP integration, and the one most often skipped. An afternoon with your malpractice carrier, your state board’s written guidance, and legal counsel pays for itself many times over.
Why practices are adding PRP now
PRP demand has grown steadily, driven by sports-medicine referrals, expanded aesthetic use, and patient preference for minimally invasive options over surgery.
Demand trends describe industry tailwinds, not a guarantee of practice-level revenue. A practice participates in that growth only if its offer, location, marketing, and operations fit the demand that exists in its specific market. Still, clinicians weighing whether to offer PRP have a reasonable case on the demand side. Patients increasingly arrive already familiar with the category, and the cash-pay dynamic, while a barrier for some, is an opportunity for practices that build a clean, transparent pricing and consent model.
Free mini course
The FDA rules behind this field, in a short, self-paced course. It costs nothing.
Get the free FDA courseEquipment: what you actually need to launch PRP
Equipment is where many practices overspend, and where a few underspend in ways that hurt outcomes. The core capital items are a medical-grade centrifuge, a diagnostic ultrasound for musculoskeletal work, and the PRP kits themselves. A handful of ancillary supplies and documentation tools round out the list.
The table below lists the core items and what drives the cost of each. Get written quotes from more than one vendor; pricing varies by vendor, region, and bundled training.
| Item | What the range looks like | Notes |
|---|---|---|
| Medical-grade centrifuge | Entry tabletop units at the low end, branded clinical units at the high end | Ask for the 510(k) letter before the quote, and confirm the kit you intend to run is validated on it |
| Diagnostic ultrasound (MSK use) | Portable handheld units at the low end, cart-based systems at the high end | Strongly recommended for joint and tendon work |
| FDA 510(k)-cleared PRP kit | A per-patient consumable; price depends on brand and volume commitment | Includes tubes, anticoagulant, and accessories |
| Individual PRP tubes | A per-tube consumable | Some protocols use multiple tubes per procedure |
| Needles, syringes, topical anesthetic, ancillary supplies | A small per-patient cost | Practice-dependent |
Kit selection deserves particular care. Before purchase, confirm the 510(k) clearance letter directly rather than relying on marketing claims. Match the kit’s target platelet concentration to your intended indications, knowing what platelet concentration the kit actually delivers, which the 510(k) summary states. Verify whether the kit supports leukocyte-rich PRP, leukocyte-poor PRP, or both, since the two profiles suit different indications. Ask whether the kit is closed-system and validated for sterility and pyrogen-free use. Ask whether it requires a proprietary centrifuge or works with universal clinical centrifuges, because that single detail can significantly change long-term economics.
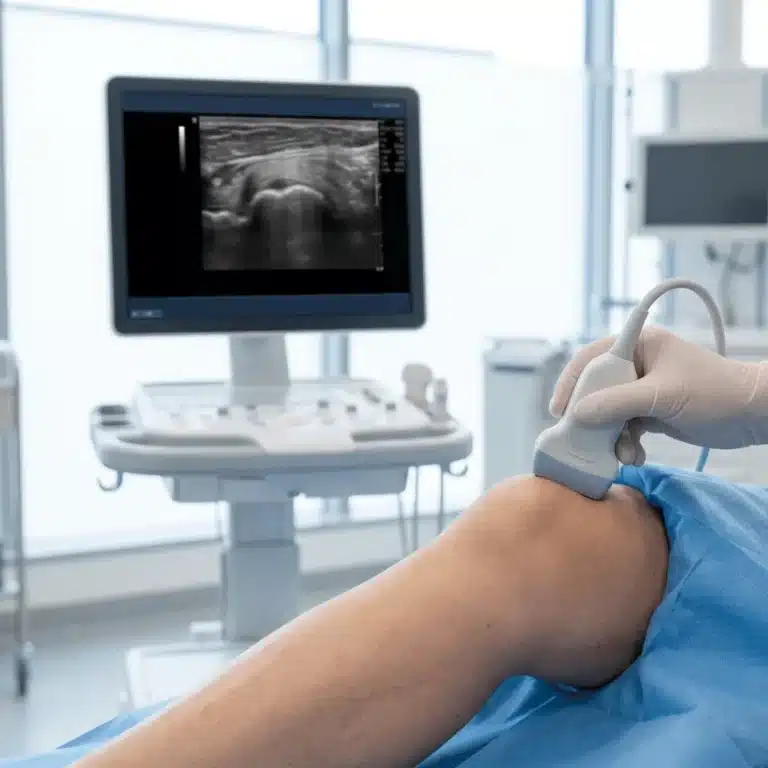
Ultrasound is not technically required for every PRP application, but it is close to required for defensible musculoskeletal work. A 2024 umbrella review of systematic reviews found ultrasound-guided injections more accurate than landmark-guided injections across joints and tendons, most consistently in the shoulder. Accuracy matters because the biologic can only work where it lands, and because ultrasound documentation strengthens the procedural note if outcomes are ever questioned.
The ancillary layer is easy to forget in a budget. You need phlebotomy supplies, a trained phlebotomist or medical assistant, appropriate refrigeration, sharps disposal, OSHA bloodborne-pathogen compliance, state-compliant medical waste handling, and EMR templates for PRP consent, procedure notes, and outcome tracking. None of these items are expensive individually, but collectively they are the difference between a clean operation and a chaotic one.
What this means in practice: spend more time vetting the kit than the centrifuge. The centrifuge is a commodity; the kit determines what biologic you actually deliver, and whether you can build a consistent, indication-matched protocol around it.
Training: what “good” looks like
Training is where the biggest variance between PRP practices shows up, and it is the variable most correlated with outcomes and compliance safety. There is no federal PRP certification that is legally required. There is, however, a strong operational reason to document training thoroughly. Malpractice carriers and hospital credentialing committees often request training documentation when a clinician adds a new procedural service line, and a well-documented training record is one of the cleanest ways to answer that request.
A strong PRP training program covers several layers at once. It starts with platelet biology and the growth-factor cascade (including PDGF, TGF-beta, VEGF, EGF, and IGF-1), which gives clinicians the mental model they need to choose preparations intentionally rather than by habit. It covers patient selection, contraindication screening, and informed consent for off-label use. It teaches venipuncture and anticoagulant selection, centrifuge protocols and concentration math, and the injection techniques appropriate to each indication, including intra-articular, peri-tendinous, and tendon-fenestration approaches for MSK, facial and scalp techniques for aesthetics, and sexual-health applications where state scope permits. Hands-on ultrasound scanning and real-time needle tracking, both in-plane and out-of-plane, separates didactically trained clinicians from procedurally competent ones. Good programs also include adverse-event recognition and management, documentation standards, compliant marketing language, and practice-integration topics such as pricing, scheduling, and outcome tracking.
The format mix matters. Didactic and e-learning content builds the foundation in biology, regulation, and preparation science. Hands-on, live-patient experience under faculty supervision develops procedural judgment in ways that no video can replicate. When comparing programs, look closely at how much supervised live-patient time each one actually includes, and at how the training record is documented, because that record is what malpractice carriers and credentialing committees ask to see.
For clinicians building or refining their skills, hands-on orthobiologic and MSK training courses provide the live-patient experience and structured feedback needed to translate evidence into reproducible practice. Didactic foundations can be covered in regenerative medicine e-learning courses that complement in-person training. Clinicians planning to offer aesthetic PRP will often benefit from cosmetic regenerative medicine training focused specifically on facial, scalp, and skin applications. Plan on more training than you think you need, document it thoroughly, and favor programs that include supervised live-patient experience.
Building the patient journey: intake through follow-up
A PRP integration that works day to day is really a well-designed patient journey. It starts with a structured intake form that captures indication, symptom duration, prior treatments, medications (especially anticoagulants and NSAIDs), oncology and autoimmune history, and recent labs including a complete blood count when clinically indicated. Contraindication screening at this stage prevents most of the problems that would otherwise surface later.
Informed consent is the next step and deserves specific attention. Written consent should clearly state the off-label nature of the procedure, acknowledge that evidence is mixed and outcomes vary, list realistic risks and common post-injection experiences, disclose the cash-pay price in writing, and avoid any language that implies a guaranteed result. Many practices find it useful to read key consent points aloud with the patient rather than handing over a form to sign, both to improve comprehension and to document a substantive conversation.
The procedure itself is short. Actual injection time is typically five to ten minutes. Total chair time, however, usually runs 45 to 75 minutes when you include intake, blood draw, spin time, preparation, the procedure, and post-procedure education. Building scheduling templates around the realistic total, rather than the injection time alone, prevents the cascading delays that sour patient experience.
Post-procedure, give patients a written discharge handout that reinforces the NSAID guidance you established earlier, explains the expected timeline of soreness (commonly one to three days) and gradual response (over weeks), and sets up a clear follow-up. A validated outcome measure, such as a joint-specific score or visual analog scale, creates the longitudinal dataset you will eventually need to evaluate your own protocols honestly.
The financial model: what to include, and what vendors leave out
This is the part where skepticism earns its keep. Vendor-published ROI examples usually include revenue and a narrow slice of costs, and they usually leave out the costs that actually determine whether a service line is profitable. A defensible PRP financial model includes the full stack: equipment amortization, per-patient consumables, clinician and staff time at loaded labor rates, marketing and lead generation, merchant fees and chargebacks, malpractice premium increases tied to the new service line, rent and utilities attributable to the procedure room, and taxes.
Published per-session pricing
A 2024 nationwide pricing study of top U.S. orthopedic hospitals reported PRP injection prices ranging from $350 to $2,815 per session, with a median near $800 and the highest prices concentrated in the Northeast. Typical private-practice session pricing commonly falls inside that published range, with higher pricing for ultrasound-guided injections and significant variation by provider experience and region. Aesthetic and sexual-health applications often price higher than musculoskeletal injections because of the procedural packaging, branding, and patient expectations that surround them. These are market patterns, not recommendations for any specific practice. Each practice should set pricing based on its own costs, market positioning, and competitive analysis.
The practical financial planning checklist
Practices that end up with a profitable PRP line usually did a few things up front. They built a cash-pay workflow with clear written pricing, merchant services that can handle the volume, and financing options (for example CareCredit or similar) so price does not become the sole conversion barrier. They trained the scheduling and front-desk team to talk about pricing and off-label status confidently, which removes friction earlier in the funnel. They tracked outcomes using validated measures, which over time becomes both a clinical quality asset and a marketing asset in the form of honest, real data.
What this means in practice: if the numbers only work under the vendor’s assumptions, they probably do not work. Build your own model with your own costs, and stress-test it against a realistic volume curve for the first 12 to 18 months.
A composite clinical vignette: an integration that worked, and one that did not
The following are fictional composites based on patterns described in published literature and practice case studies. They do not describe real practices.
In the first composite, a mid-sized sports-medicine practice adds PRP after six months of structured planning. Two clinicians complete hands-on ultrasound training and live-patient procedural courses, and a medical assistant is cross-trained on phlebotomy and kit preparation. The practice selects an FDA 510(k)-cleared kit that supports both LR and LP preparations, standardizes its protocol by indication, builds a written consent that clearly states off-label use, and prices ultrasound-guided musculoskeletal PRP at a single transparent rate visible on the website. The first three months produce modest volume, which the practice uses to refine scheduling templates and discharge handouts. By month nine, the clinic is running a steady schedule and beginning to collect outcome data it can use for honest marketing.
In the second composite, a small aesthetic practice rushes the launch. The clinician completes a short didactic-only course, skips the hands-on ultrasound component, and orders a proprietary kit that cannot be used with an existing centrifuge. The marketing site calls PRP “FDA-approved” for hair loss. Consent is a single-page form handed to the patient at check-in. Within a year, the practice is dealing with inconsistent outcomes, a consent complaint, an advertising concern from the state board, and a kit relationship that cannot be untangled without absorbing a write-off. The clinician’s skill was never the problem. The workflow was.
The contrast is not about intelligence or talent. It is about how many of the predictable failure modes the practice designed around before going live.
Common pitfalls when launching PRP
A handful of pitfalls appear across most struggling PRP integrations. Marketing language is the most common: variations of “FDA-approved,” “cures,” or “guaranteed results” will attract regulatory attention and undermine the off-label consent conversation the rest of the practice depends on. Consent shortcuts are the second: a single-page generic form, signed at check-in without discussion, will not hold up as well as a shorter form combined with a documented conversation. Under-training is the third: clinicians who skip hands-on ultrasound often discover their accuracy gaps only after patients return with unchanged symptoms. Over-reliance on vendor financial models is the fourth: budgets that collapse once actual labor and marketing costs are added will create pressure to cut corners elsewhere, which is where compliance drift begins.
How structured training accelerates safe, compliant integration
The common thread across every section of this guide is that PRP integration is a multidisciplinary project. Structured training programs compress the learning curve by covering clinical technique, regulatory framing, workflow design, and financial modeling in one coordinated arc. They also generate the documentation that malpractice carriers, state boards, and credentialing committees ask for, which reduces administrative friction later.
For clinicians ready to build or refine their skills, the combination of hands-on procedural training and strong didactic foundations is more efficient than piecing those elements together from separate sources. Start with the introductory PRP course to see how its curriculum maps to the integration steps described above.
Frequently asked questions from clinicians
Is PRP FDA-approved for knee osteoarthritis, hair loss, or aesthetic applications?
No. PRP preparation devices are FDA 510(k)-cleared for bone graft handling. Clinical injection uses, including knee OA, tendinopathy, hair loss, aesthetic applications, and sexual-health indications, are considered off-label. Clinicians should document off-label status in written informed consent and should not use language that implies FDA approval for these uses in marketing or in patient conversations.
Will insurance cover PRP for my patients?
Almost never for MSK and aesthetic applications. Medicare coverage of PRP is limited to one wound-care indication under a national coverage determination. Commercial payers generally classify PRP as investigational and do not cover it. A few programs have provisional coverage for specific indications. The practical planning assumption is cash-pay, with transparent written pricing, merchant services that can handle the volume, and optional financing for patients who ask.
How long does it take to recoup the equipment investment?
It depends heavily on volume, pricing, and fully loaded costs. Vendor ROI examples often imply payback in months, but those examples frequently leave out labor, marketing, malpractice rider premiums, rent allocation, and credit card processing. Build a model with your own costs and stress-test it against a realistic volume ramp of 12 to 18 months before making a decision. Be especially careful about kits that lock you into a proprietary centrifuge, since the long-term economics of lock-in can be meaningfully worse than a universally compatible system.
What training is reasonable before launching PRP?
Plan on didactic foundations in platelet biology, preparation, and regulation, plus hands-on procedural training that includes ultrasound scanning and live-patient practice. Weight supervised live-patient practice heavily when comparing programs. Document the training thoroughly and keep copies for credentialing and malpractice requests. Consult your state board on scope-of-practice for mid-level providers, and confirm malpractice coverage with your carrier before seeing your first PRP patient.
How should we price PRP?
Pricing should reflect your fully loaded costs, local market, and positioning rather than a single national benchmark. Published ranges span roughly $350 to $2,815 per session for musculoskeletal applications, with higher pricing common for aesthetic and sexual-health applications. Transparent, written, pre-procedure pricing disclosure is both good consumer practice and useful compliance hygiene.
What should we do about marketing language?
Avoid “FDA-approved,” “cures,” “heals,” “guaranteed,” and “100% safe” without qualification. Use “FDA 510(k)-cleared device used off-label,” “studied for symptom support in,” “evidence is mixed,” “individual results vary,” and similar language. Treat testimonials and reviews per FTC rules, which include clear disclosure of material connections and avoidance of suppressing honest negative reviews. Your marketing site is the first document a regulator or plaintiff attorney will read.
How do we handle a patient whose prior PRP injection somewhere else did not work?
Start by reviewing the prior workflow, including the kit, imaging guidance, medication use around the injection, and post-procedure instructions. A candid conversation about what is known, what is uncertain, and what individual response factors look like helps patients decide about a second attempt. Document the conversation and the informed consent carefully.
Key takeaways
- Adding PRP is a regulatory, operational, and financial project, not just an equipment purchase.
- PRP preparation systems are FDA 510(k)-cleared for bone graft handling; clinical injection uses are off-label and require clear informed consent.
- Reimbursement is minimal outside narrow indications; PRP is overwhelmingly cash-pay.
- Scope-of-practice rules vary by state and provider type, so verify with your state board and malpractice carrier before launch.
- Equipment selection should prioritize the FDA 510(k)-cleared kit, kit-centrifuge compatibility, and diagnostic ultrasound capability for MSK work.
- Strong training combines didactic foundations, hands-on procedural practice, and a documented record of supervised training that malpractice carriers and credentialing committees ask to see.
- Build your financial model with fully loaded costs; vendor ROI tables are illustrative, not projections.
- A transparent cash-pay workflow, careful consent, and compliant marketing language are the operational backbone of a defensible PRP service line.
RMA Disclosure
Regenerative Medicine Academy (RMA) is an education company that provides clinician training in some of the techniques discussed in this article. This content is educational and does not constitute a claim of clinical superiority, a guarantee of outcomes, or a substitute for individual clinical judgment.
For clinicians ready to take the next step
Clinicians evaluating a PRP launch, or refining an existing service line, can explore hands-on curriculum, didactic foundations, and aesthetic-focused programs through RMA. Visit the RMA course catalog to find the track that matches your integration goals.
When you are ready to move from planning to practice, the course catalog lays out the hands-on options, and a short conversation will scope which format fits your practice.
The course that goes with this post
PRP training
Every PRP course in one place, from the first draw to aesthetics and sexual health, private and hands on.
Important information
Education, not medical advice
Regen Med Academy provides education and training for licensed healthcare providers. Everything on this site is for educational purposes only. It is not medical advice, not a treatment recommendation, and not an offer to treat. Providers are responsible for practicing within the scope of their own license and their own state law.
Where a course can run
Courses are taught only in states where the modality is legal for the license you hold. State law in this field changes, sometimes more than once a year. Our reading of each state, with its sources and the date we checked, is on the rules by state page. It is a starting point, not legal advice. It is your responsibility to confirm the modality is legal in your state for your license. Do that before you book. The authority on your own scope is your licensing board, not us. State medical board contact details are published by the Federation of State Medical Boards.
Training on live patients
Procedures performed during training are performed on consenting patients, by licensed providers, under supervision. Participation is voluntary and outcomes vary.
Products and modalities
Some products and modalities discussed in these courses are not FDA approved or cleared for the uses described. Regen Med Academy does not manufacture, sell or endorse any product, and does not approve or clear any product. The FDA publishes guidance for patients and providers on regenerative medicine therapies.
What a certificate is, and is not
Regen Med Academy does not offer CMEs, credit hours or accreditation of any kind. What you receive is a Certificate of Completion. It records that you attended and performed the procedures under supervision. It is not a license, not a board certification, and it does not expand your scope of practice.
Coverage is yours to arrange
You are responsible for your own malpractice coverage. We will help you work out what to ask your carrier, and we recommend getting the answer in writing. Regen Med Academy does not provide, arrange or extend coverage to trainees, and nothing on this page is legal advice or an assurance of coverage.