
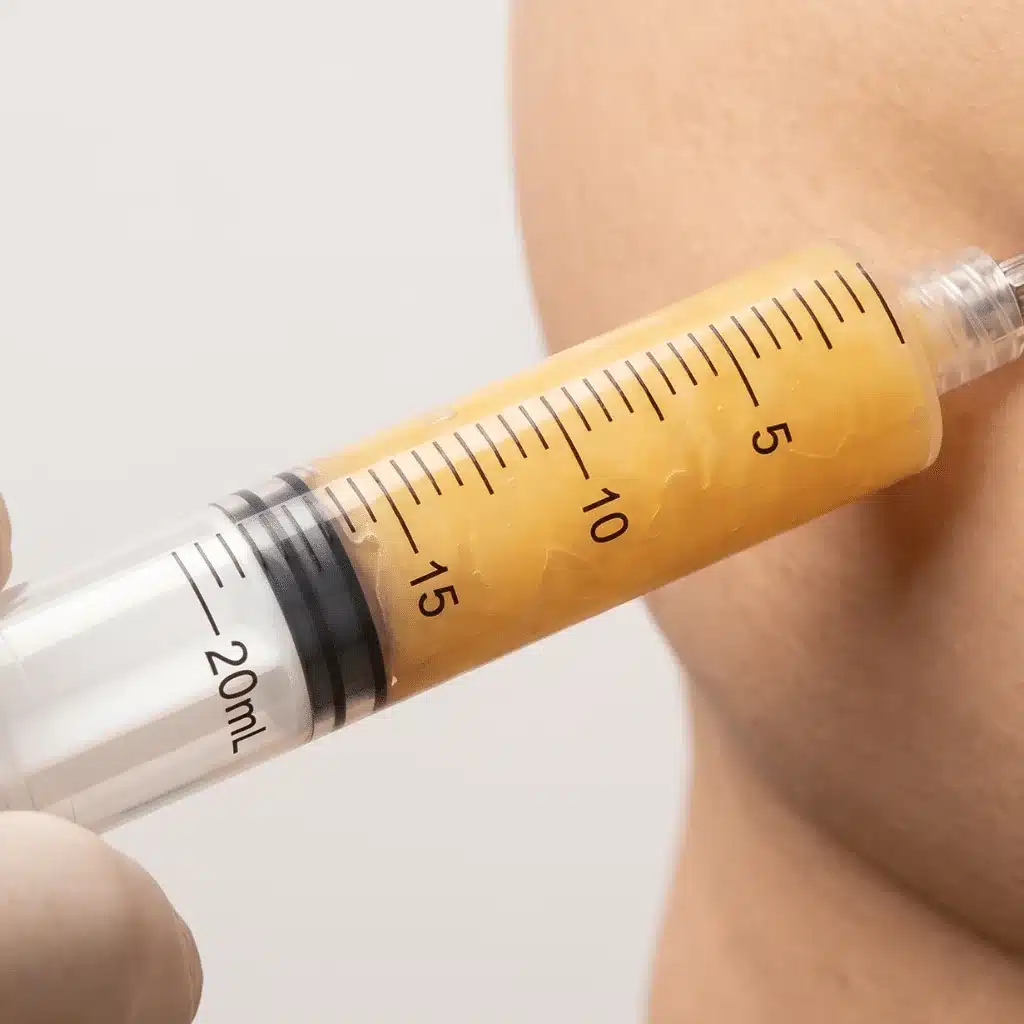
Adipose tissue is one of the most versatile autologous sources in regenerative medicine, but it is also one of the most regulated, and the regulatory rules shape every clinical decision that follows. This guide walks through the biology, harvesting and processing techniques, clinical applications, safety profile, and training requirements, with the regulatory framing placed first because it determines what is legally and clinically defensible in practice. The thread running through all of it is simple: match your technique to the regulatory framework, and match your marketing to the evidence.
In short: Adipose tissue contains a rich mix of cells and matrix, including adipose-derived stem cells within what is called the stromal vascular fraction (SVF), which makes it a practical autologous source for regenerative applications. The single most important regulatory line in this field is the difference between mechanical processing (legal in the United States within the established framework) and enzymatic processing (not legal as a clinical treatment in the United States). MFAT, microfat, and nanofat are mechanical preparations that break adipose tissue into smaller pieces without enzymes; they sit in the legal mechanical-processing pathway. Enzymatic SVF, produced by digesting adipose tissue with collagenase, is regulated by FDA as a drug. Two federal appeals courts, the Eleventh Circuit in 2021 and the Ninth Circuit in 2024, have ruled for FDA in cases against clinics that offered it, and clinic-prepared SVF offered as a treatment is not legal in the United States outside of an authorized clinical trial. RMA’s adipose training covers mechanical MFAT processing and does not cover SVF preparation or clinical use. Outcomes vary in every patient.
Important Disclaimer
Regenerative Medicine Academy (RMA) is an education company providing training for licensed clinicians. This article is educational content only and does not constitute medical, legal, business, tax, or financial advice, nor a guarantee of clinical or financial outcomes. Adipose tissue harvesting, processing, and reinjection are subject to FDA regulation, state scope-of-practice rules, and professional society standards. Many techniques discussed are used off-label. Enzymatically digested SVF is considered a drug by the FDA and clinic-prepared SVF offered as a treatment is not legal in the United States; RMA does not train on SVF. Clinicians are responsible for verifying FDA device and biologic status, state scope-of-practice requirements, informed consent obligations, malpractice coverage, corporate-practice-of-medicine rules, and applicable advertising laws before performing any adipose-based procedure. Individual clinical results vary. Consult qualified legal, compliance, and medical professionals before acting.
Adipose tissue has a long history in medicine, starting as a surgical problem (how to get rid of it) and evolving into a surgical resource (how to harvest and use it carefully). Over the past two decades, cellular and regenerative science has added another chapter, one where the same fat that surgeons once discarded is now studied as a source of therapeutic cells, extracellular matrix, and growth factors.
The excitement around adipose-based regenerative medicine is real, and so is the potential for a practice to get in trouble. The same modality can sit in very different regulatory boxes depending on how it is processed. A clinician who understands this map can build a legally defensible, clinically credible service line. A clinician who does not can inadvertently step into enforcement risk, malpractice exposure, and marketing language that invites regulatory letters.
Why adipose tissue?
The biology in plain language
Adipose tissue is more than stored energy. Mature adipocytes (the cells that store fat) are only part of the cell population in fat. The rest are a mixed population of blood-derived cells, pericytes (cells that surround small blood vessels), smooth muscle cells, endothelial cells, immune cells, and, most relevant to regenerative work, adipose-derived stem cells within the stromal vascular fraction.
Three practical features make adipose attractive as an autologous source. It is plentiful, even in lean patients. It is accessible through relatively standardized liposuction technique. And it contains mesenchymal-type cells in its stromal vascular fraction.
No adipose-derived stem cell product is FDA approved. FDA’s page on regenerative medicine therapies (content current as of April 8, 2024) lists “stromal vascular fraction (fat-derived cells)” among unapproved products, and the only stem cell products FDA has approved are cord blood hematopoietic progenitor cells for certain blood disorders.
It is worth pausing on the vocabulary, because the words are not interchangeable, and U.S. regulators treat them differently. Autologous fat graft refers to fat moved from one site to another in the same patient. Microfat and nanofat are mechanically processed preparations used mostly in aesthetic applications. Microfragmented adipose tissue (MFAT) is fat that has been broken down into smaller clusters through a closed-system mechanical device, without enzymes. Stromal vascular fraction (SVF) is what you get when you digest adipose tissue with an enzyme like collagenase: a concentrated, cell-rich aqueous fraction. Adipose-derived stem cells (ADSCs) are a purified or culture-expanded population of cells isolated from the SVF. These terms describe a gradient, from whole tissue at one end to isolated cells at the other, and the gradient maps almost perfectly onto how the FDA categorizes these products.
The regulatory reality clinicians must understand first
The single most important question in this field is mechanical or enzymatic. That one distinction sits at the center of what U.S. clinicians can legally offer to patients.
The framework: minimally manipulated and homologous, or not
Under Section 361 of the Public Health Service Act and 21 CFR Part 1271, human cells, tissues, and cellular and tissue-based products (HCT/Ps) that meet four criteria are regulated as tissue rather than as drugs. The four criteria are in 21 CFR 1271.10(a). The product must be minimally manipulated. It must be intended for homologous use only, meaning the same basic function the tissue served in the donor. It must not be combined with another article, apart from a short list such as water, crystalloids or a preserving agent. And it must either have no systemic effect and not depend on the metabolic activity of living cells, or be for autologous use, use in a first-degree or second-degree blood relative, or reproductive use. A separate provision, 21 CFR 1271.15(b), covers an establishment that removes tissue from a patient and implants it into the same patient during the same surgical procedure. Products that meet the four criteria do not require pre-market FDA approval, though establishment registration and good tissue practices may still apply.
Under 21 CFR 1271.20, an HCT/P that does not meet the criteria in 1271.10(a), and does not qualify for an exception in 1271.15, “will be regulated as a drug, device, and/or biological product” under the Federal Food, Drug, and Cosmetic Act and/or section 351 of the Public Health Service Act. For unapproved cell products, stromal vascular fraction among them, FDA’s patient and consumer page (content current as of April 8, 2024) says they “require FDA licensure/approval to be marketed to consumers” and, before approval, require “FDA oversight in a clinical trial.”
In practical terms, the FDA looks at how the tissue is processed and what it is used for. Its guidance on minimal manipulation and homologous use considers processing that breaks adipose tissue down to isolate its cells, enzymatic digestion included, to be more than minimal manipulation. Mechanical processing that keeps the tissue’s structure does not settle the question by itself. Homologous use and the device’s cleared indication still apply.
Mechanical processing: no enzymes
MFAT, microfat, and nanofat are all mechanical processing approaches. They differ in particle size, intended application, and the specific equipment used, but they share the same key feature for U.S. regulatory purposes: none of them use enzymes.
MFAT is typically produced through a 510(k)-cleared closed-system mechanical device. When we checked FDA’s 510(k) record for one such device, K171135, on November 4, 2026, it showed a Class II suction lipoplasty system “intended for the closed-loop processing of lipoaspirate tissue” in listed surgical specialties, orthopedic and arthroscopic surgery among them. Its indications add that harvested fat “is only to be used without any additional manipulation.” RMA does not recommend any device. Microfat is a smaller-particle mechanical preparation often used for aesthetic facial work. Nanofat is mechanically emulsified through syringe-to-syringe shuffling and filtration to produce a cell-rich, largely matrix-depleted fluid used for skin quality and superficial applications. The common thread across all three is that the tissue is broken into smaller pieces by physical means, with no enzymatic digestion involved.
Mechanical processing avoids the enzymatic digestion that the FDA considers more than minimal manipulation. That does not settle how a given use is regulated. Homologous use and the device’s cleared indication still apply. Use of MFAT for a specific named indication like knee osteoarthritis is off-label unless and until FDA clears that indication. Marketing language matters here: “510(k)-cleared device used to process adipose tissue” is accurate; “FDA-approved for knee osteoarthritis” is not. The two statements are not close substitutes legally.
Enzymatic SVF: not legal in the United States
SVF is fundamentally different. It is produced by digesting adipose tissue with an enzyme (typically collagenase) to release a cell-rich aqueous fraction. FDA’s guidance on minimal manipulation and homologous use says adipose tissue processed to isolate its cellular components, for example by enzymatic digestion, “generally is considered more than minimally manipulated.” A product that fails a 1271.10(a) criterion and fits no exception in 1271.15 is regulated under 21 CFR 1271.20 as a drug, device, and/or biological product.
Two federal appeals courts have ruled for FDA in SVF cases. In U.S. v. US Stem Cell Clinic (2021), the U.S. Court of Appeals for the Eleventh Circuit affirmed a judgment that barred a clinic from offering its SVF procedure until it could show FDA that the therapy is safe and effective. The court held that the same-surgical-procedure exception “unambiguously does not apply” and agreed that the clinic did not intend the SVF “solely for homologous use.” In U.S. v. California Stem Cell Treatment Center (2024), the U.S. Court of Appeals for the Ninth Circuit held that the defendants’ SVF is a “drug” under the Federal Food, Drug, and Cosmetic Act, rejected the argument that the same-surgical-procedure exception applies, and reversed the lower court.
In plain language: clinic-prepared enzymatic SVF offered as a treatment for any indication is not legal in the United States outside of an authorized clinical trial conducted under an Investigational New Drug application. Ask your attorney how these rulings apply where you practice.
What RMA’s training covers
For these reasons, RMA’s adipose-tissue training programs cover mechanical MFAT processing and do not cover SVF preparation or clinical use. The reasoning is direct: U.S. clinicians cannot legally offer clinic-prepared SVF as a treatment, so training on SVF preparation does not translate into a legally defensible service line. RMA’s curriculum focuses on the techniques that clinicians can actually use in U.S. practice today.
The table below summarizes how the major adipose-based product categories map to their regulatory pathway and to compliant language. Its status column rests on 21 CFR 1271.10(a), 21 CFR 1271.20, FDA’s guidance on minimal manipulation and homologous use, the 510(k) record cited above and the two appellate opinions. It is a summary, not legal advice; confirm a specific product’s status with counsel.
| Product type | FDA regulatory status | Compliant framing |
|---|---|---|
| Autologous fat graft (structural, Coleman-style) | 361 HCT/P only if it meets every 1271.10(a) criterion; FDA’s guidance counts filling facial voids and breast reconstruction or augmentation as homologous uses | “Autologous fat grafting,” “minimally manipulated autologous adipose” |
| Microfat or nanofat (mechanical processing) | Depends on the processing steps and the intended use. FDA’s guidance says adipose processed to isolate its cells, by enzymes or by mechanical disruption, generally is more than minimally manipulated. Confirm with counsel | “Mechanically processed autologous adipose,” “microfat,” “nanofat” |
| MFAT via 510(k)-cleared device | Class II device, 510(k) cleared (for example K171135). The clearance covers the device and its listed uses, not a treatment | “510(k)-cleared device used to process adipose tissue,” off-label for specific indications |
| Enzymatic SVF prepared in clinic | More than minimally manipulated under FDA’s guidance; regulated as a drug and biological product under 21 CFR 1271.20; see the two appellate opinions above | “Investigational only; FDA classifies as a drug requiring approval” |
| Culture-expanded adipose-derived stem cells | More than minimally manipulated under FDA’s guidance; regulated as a drug and biological product under 21 CFR 1271.20 and section 351 of the PHS Act | “Investigational only” |
The FDA 510(k) Premarket Notification database is the primary source for verifying the cleared scope of any specific device. Reading the cleared indication in a 510(k) record is also a useful corrective: cleared indications are typically narrower than how devices are sometimes marketed.
What this means in practice: regulatory framing is not an afterthought. It determines which products you can legally offer, how you can describe them, and what consent language you need. Clinicians building an adipose-based service line should anchor on this framing before they decide on a cannula.
Free mini course
The FDA rules behind this field, in a short, self-paced course. It costs nothing.
Get the free FDA courseHarvesting techniques: the mechanics of moving fat safely
Once the regulatory foundation is in place, the harvesting conversation can begin. Every regenerative adipose technique starts with tumescent anesthesia, followed by a liposuction method chosen to match the intended end product, followed by a processing method that affects how the product is regulated.
Tumescent anesthesia
Tumescent anesthesia involves infiltrating a large volume of dilute lidocaine and epinephrine in isotonic crystalloid into the subcutaneous tissue before aspiration. Tumescent lidocaine dosing differs from plain-lidocaine dosing, and this post does not give it. It is taught in the course under the instructor’s protocol and published guidelines.
Two pharmacology points matter for safe practice. First, absorption is slow. In a 2016 study of tumescent lidocaine by Klein and Jeske, serum lidocaine peaked at a mean of 12.5 hours after infiltration with liposuction and 13.1 hours without it, so the highest blood levels, and the risk of local anesthetic systemic toxicity (LAST), can come after the patient has left the procedure room. Second, the same paper names drugs that slow lidocaine metabolism by inhibiting the liver enzymes cytochrome P450 3A4 and 1A2, such as erythromycin, sertraline, fluconazole and ciprofloxacin. A careful medication review is part of adipose harvest, not a formality.
Liposuction methods for regenerative harvest
Suction-assisted lipoaspiration (SAL) is a common approach for adipose harvest in regenerative work. Power-assisted liposuction (PAL) adds mechanical cannula oscillation to reduce operator fatigue in high-volume harvests. How each method affects the cells in the graft is still a research question, so choose a method on purpose and record it.
For aesthetic volumization, the Coleman structural fat grafting technique remains the reference standard: low-pressure syringe aspiration through 2 to 3 mm cannulas, followed by centrifugation. Microfat harvest uses low suction pressures through specialized small-bore multiport cannulas to produce a finer graft suitable for delicate facial work. Nanofat preparation mechanically emulsifies the graft through syringe-to-syringe shuffling and filters it through nylon membranes to produce a cell-rich, largely matrix-depleted fluid used for skin-quality applications.
MFAT harvest feeds directly into a 510(k)-cleared closed-system device that mechanically fragments the tissue without enzymes, producing clusters small enough for injection through a smaller-bore needle.
The table below summarizes the main harvest techniques, their typical applications, and what each one involves.
| Technique | Typical application | What it involves |
|---|---|---|
| Suction-assisted lipoaspiration (SAL) | Standard for regenerative adipose harvest | Cannula under suction |
| Power-assisted liposuction (PAL) | High-volume regenerative or aesthetic harvest | Cannula with mechanical oscillation, used to reduce operator fatigue |
| Coleman structural fat grafting | Aesthetic volumization | Low-pressure syringe aspiration, 2 to 3 mm cannulas, centrifugation |
| Microfat | Fine aesthetic grafting | Low suction pressure through specialized small-bore multiport cannulas |
| Nanofat | Skin quality and superficial applications | Mechanical emulsification and filtration; cell-rich, largely matrix-depleted |
| MFAT through 510(k)-cleared device | Orthopedic and other tissue-handling applications | Closed-system mechanical fragmentation without enzymes |
Donor sites and harvest volume
Common donor sites include the abdomen, flanks, thighs, hips, and back. Harvest volume depends on the intended product and the target, with larger volumes for volumetric aesthetic grafting, and your protocol sets it. Patient-specific factors shape the realistic volume: body composition, prior abdominal surgery, connective tissue characteristics, and bleeding risk all influence both yield and safety.
Processing methods: where biology meets regulation
Processing is where the regulatory pathway becomes concrete. The same aspirate can stay within the legal mechanical-processing framework or move into the illegal enzymatic-drug framework depending on what you do to it next.
Decantation and washing are the simplest mechanical approaches, separating blood and tumescent fluid from the fat by gravity or gentle agitation. They produce variable graft quality and are used mostly as a prelude to other steps. Centrifugation, popularized by Coleman, separates the aspirate into layered fractions and concentrates the usable fat layer. Mechanical emulsification methods, including the family of nanofat, SEFFI, and SNIF preparations, use syringe-to-syringe shuffling and filtration to break down the graft without enzymes. Closed-system MFAT devices mechanically fragment the tissue through defined internal geometries to produce a consistent microfragmented product for tissue handling.
All of these are mechanical processing methods. None of them use enzymes. They sit within the legal U.S. regulatory framework, either under the 361 tissue exception when the four criteria are met, or as the output of a 510(k)-cleared device used within its cleared scope.
Enzymatic digestion with collagenase is the line that changes everything. Adding a digestive enzyme to break down adipose tissue and release a cell-rich aqueous fraction (SVF) is what the FDA considers more than minimal manipulation, with the regulatory and court consequences set out earlier in this post.
Some newer mechanical-only methods (sometimes called M-SVF or SVM) aim to produce SVF-like cell-rich fractions without enzymes, generally at lower cell yields. The regulatory status of any specific mechanical SVF approach depends on its particular processing steps and how the FDA characterizes it. Clinicians considering these methods should verify the FDA framing for the specific system, consult counsel before marketing, and not assume that “mechanical” automatically removes regulatory questions in this gray area.
What this means in practice: the processing decision is not purely a clinical one. It is the single choice that most clearly determines whether your service line uses mechanical processing (MFAT, microfat, nanofat) or sits in territory that FDA regulates as a drug (enzymatic SVF). RMA’s adipose training covers mechanical MFAT processing and does not cover SVF preparation.
Clinical applications: what the published evidence supports, and what it does not
Adipose-based regenerative applications span musculoskeletal, wound care, aesthetic, and emerging uses. Evidence quality varies significantly across categories, and accurate framing matters for each.
In musculoskeletal medicine, some clinicians use MFAT for knee osteoarthritis. That use is off-label, and it stays off-label unless and until FDA clears that indication. FDA’s guidance on minimal manipulation and homologous use also says an adipose HCT/P used to treat arthritis “by regenerating or promoting the regeneration of articular cartilage or tendon” is “generally not considered a homologous use.” The evidence on MFAT for knee osteoarthritis is not settled. The 2026 ACR guideline update, approved by the ACR Board of Directors on September 8, 2026 and published as a summary ahead of the full papers, says “In people with knee and hip OA, we strongly recommend against stem cell injections”; the summary does not say whether it counts adipose preparations such as MFAT in that group. Broader orthobiologic context is available through the American Academy of Orthopaedic Surgeons, whose Orthobiologics Registry, announced in December 2025, is gathering real-world outcome data on knee osteoarthritis orthobiologic interventions. Related professional society work, including the 2024 ESSKA-ORBIT consensus, shapes how clinicians think about orthobiologics in knee osteoarthritis more broadly.
In wound healing, adipose-derived products are being studied for chronic and refractory wounds. This use is investigational. According to FDA’s page on regenerative medicine therapies (content current as of April 8, 2024), the only stem cell products FDA has approved are cord blood hematopoietic progenitor cells for certain blood disorders.
In aesthetic and plastic surgery, autologous fat grafting has a long clinical track record for facial volumization, periorbital rejuvenation, breast reconstruction, and other volume-restoration indications. FDA’s guidance counts using fat to fill voids in the face or hands, and transplanting it into the breast for reconstruction or augmentation, as homologous uses. Microfat and nanofat are finer mechanical preparations used in facial and superficial skin work. Their regulatory status depends on the processing steps and the intended use, so confirm it with counsel before you offer or advertise them. How much grafted volume lasts over time varies and is not settled.
What this means in practice: when you describe clinical applications to patients or in marketing, match your language to the evidence tier for each indication. A long-used technique like facial fat grafting calls for different language than an investigational use like a chronic wound. Blanket “stem cell therapy” language blurs those distinctions in exactly the way regulators object to.
Safety profile: what the literature reports
Safety of adipose harvest and adipose-based therapies can be discussed at two levels: the mechanical safety of the harvest itself, and the biological safety of the product being reintroduced.
Lipoaspiration safety depends heavily on technique, tumescent management, and patient selection. A 2009 patient safety advisory on liposuction from the American Society of Plastic Surgeons lists minor complications that “resolve on their own or with little additional treatment,” such as small hematomas, seromas and minor contour irregularities. It lists more severe ones, including skin perforation, vital organ injury, adverse anesthesia reaction, major hemorrhage, deep vein thrombosis, pulmonary embolism and fat embolism, and it calls infection “one of the more serious complications of liposuction.” The same advisory notes that lidocaine toxicity “can present as cardiac and neurologic complications,” which is one reason to take tumescent dosing and drug interaction screening seriously.
Safety data are only as good as the way adverse events are recorded, so log adverse events in a structured way from the first case rather than relying on passive reporting.
What should consent for an off-label adipose procedure cover?
Here is what a consent conversation for an off-label mechanical adipose procedure should cover: the device’s cleared indication from its 510(k) record, a plain statement that the planned use is off-label, the harvest and injection risks, the alternatives, what the evidence does and does not show, and how the practice will record outcomes and adverse events. For a joint, add that FDA’s homologous use guidance generally does not consider adipose used to regenerate cartilage in arthritis a homologous use. A signed consent form does not change how a product is regulated.
Training: what a defensible pathway looks like
A credible adipose-harvesting training pathway covers clinical technique, pharmacology, regulation, and practice integration. On the clinical side, that means patient selection and preoperative screening, tumescent pharmacology and LAST recognition, sterile technique and procedure-room setup, cannula selection and harvest technique across indication types, processing decisions and their regulatory implications, injection technique across anatomic targets, and emergency management for both local and systemic complications. On the operational side, it means informed consent, documentation, advertising compliance, outcome tracking, and adverse event logging.
RMA’s adipose-tissue curriculum is built around mechanical processing. When we checked the Adipose and MFAT Tissue Harvesting course page on November 4, 2026, it listed the science of adipose and MFAT, donor site selection, harvest and mechanical processing, operation of closed adipose processing systems, liposuction technique using local anesthetic, injection methods including intraosseous principles, and case review on the regulatory boundaries for adipose-derived procedures. RMA does not provide training on enzymatic SVF preparation or clinical use.
The format mix matters. Didactic learning builds the biology, pharmacology, and regulation foundation. Live-patient, supervised practice develops the cannula handling, tumescent infiltration technique, and processing workflow that simulation cannot fully replicate. When we checked its page on November 4, 2026, RMA’s hands-on musculoskeletal regenerative medicine training included the Adipose and MFAT Tissue Harvesting course. Training gives you supervised cases and a method. It does not guarantee a clinical result. Didactic foundations can be covered in regenerative medicine e-learning courses. When we checked it on the same date, RMA’s cosmetic regenerative medicine training listed PRP for Aesthetics and Hair Loss and Bio-Fillers with Plasma Gel, not fat grafting.
Before you add an adipose service, ask your malpractice carrier whether your policy covers the procedure and what records it wants. If you hold hospital privileges, ask the credentialing committee what it requires. The carrier and the committee decide; a training record does not settle either question.
Common pitfalls when integrating adipose-based services
A few patterns appear across struggling adipose-based service lines.
A serious legal exposure in U.S. practice is offering clinic-prepared enzymatic SVF as a treatment, for the regulatory reasons and court rulings set out earlier in this post. RMA does not train on SVF.
Another pitfall is marketing language that implies FDA approval for off-label indications, or that blurs the line between a 510(k)-cleared device and an approved indication. Saying a 510(k)-cleared closed-system device is “FDA-approved for knee osteoarthritis” is regulatorily inaccurate and creates exposure even when the underlying procedure is mechanically and clinically sound. Related to this is treating the words “stem cells,” “SVF,” and “MFAT” as interchangeable. They are not. They sit in different regulatory categories, and using them as synonyms creates both clinical confusion and regulatory risk.
Other common pitfalls include inadequate tumescent pharmacology (including insufficient attention to delayed lidocaine peaks and CYP3A4 interactions), single-page generic consent that will not hold up if outcomes disappoint, and a failure to track outcomes with validated measures, which leaves the practice without defensible internal data when questions arise.
What structured training should cover
Each of the pitfalls above is a training gap as much as an operational one. A strong program covers the regulation behind marketing language, the pharmacology of tumescent infiltration, harvest and injection technique, and the documentation the practice will need later. Training gives you supervised cases and a method. It does not guarantee a clinical result.
Clinicians evaluating an adipose-based integration, or refining an existing one, can explore hands-on curriculum, didactic foundations, and aesthetic-focused programs through RMA. The curriculum design reflects the integrated nature of the work: regulation, biology, technique, and workflow taught together rather than as separate modules, and built around the legal mechanical-processing pathway that U.S. clinicians can actually use.
Frequently asked questions from clinicians
Is adipose-based regenerative therapy FDA-approved for knee osteoarthritis or other musculoskeletal conditions?
No. Closed-system MFAT devices are 510(k)-cleared devices, not approved treatments. One such clearance, K171135, covers closed-loop processing of lipoaspirate in listed surgical specialties, orthopedic and arthroscopic surgery among them. Use for a specific indication like knee osteoarthritis is off-label unless and until FDA clears that indication. Marketing should describe the device accurately as “510(k)-cleared for adipose tissue handling” and should not imply FDA approval for named conditions.
What is the legal status of enzymatic SVF prepared in a clinic, and does RMA train on it?
Clinic-prepared enzymatic SVF is not legal in the United States as a clinical treatment. FDA regulates enzymatically digested SVF as a drug: it needs FDA approval before it is marketed, and before approval it can be given only in a clinical trial under FDA oversight. Two federal appeals courts have ruled for FDA in SVF cases, the Eleventh Circuit in 2021 and the Ninth Circuit in 2024. Offering enzymatic SVF as a treatment for any indication outside of an authorized clinical trial sits outside what the FDA and federal courts have said is legally permissible. RMA does not train on SVF preparation or clinical use, because U.S. clinicians cannot legally offer it. Practices considering any SVF-related service should consult counsel before proceeding.
How does MFAT differ from SVF and from culture-expanded ADSCs?
MFAT is adipose tissue mechanically fragmented into smaller clusters, without enzymes, through a closed-system device. Microfat and nanofat are also mechanical preparations, used mostly in aesthetic applications. SVF is an enzymatically prepared aqueous fraction concentrated in cells. Culture-expanded ADSCs are a purified, expanded cell product. The mechanical preparations (MFAT, microfat, nanofat) avoid enzymatic digestion, though homologous use and the device’s cleared indication still decide how a given use is regulated. Enzymatic SVF and culture-expanded ADSCs are regulated as drugs, outside of an authorized clinical trial. Using these terms as synonyms is both clinically imprecise and regulatorily dangerous.
What does the literature say about tumescent lidocaine dosing?
This post does not give dosing. Tumescent lidocaine dosing is taught in the course under the instructor’s protocol and published guidelines. The dose ceiling depends on technique and patient factors. In a 2016 study by Klein and Jeske, serum lidocaine peaked many hours after infiltration, and the same paper names drugs that inhibit cytochrome P450 3A4 and 1A2 as one reason lidocaine metabolism can be too slow. Clinicians should work from published formulations, calculate doses patient by patient, and monitor for LAST signs during and after the case.
Which harvesting technique should we choose?
Match technique to product. For volumetric aesthetic grafting, Coleman-style harvest remains the reference. For fine facial work, microfat. For skin quality and superficial applications, nanofat. For musculoskeletal use of a device-based product, MFAT through a 510(k)-cleared closed-system device. Working backward from the intended end product is more useful than picking a favorite harvest method and trying to make every indication fit it.
How do we handle marketing for adipose-based services?
Use precise language. “510(k)-cleared device used to process adipose tissue,” “off-label for specific indications,” “evidence is mixed and individual results vary,” and “autologous tissue” are more accurate framings. No phrase is safe by itself: have counsel review your ads, and use the rules by state page to check whether your state requires a stem cell notice in ads. When we checked on November 4, 2026, Google’s advertising policy did not allow ads that promote cell or gene therapies, naming stem cell therapy, cellular (non-stem) therapy and PRP among its examples, with narrow exceptions for FDA-approved products and purely educational ads. Avoid “FDA-approved,” “cures,” “guarantees,” and “stem cell therapy” used as a generic synonym for any adipose product. Apply the FTC’s Endorsement Guides and its Consumer Reviews and Testimonials Rule, including clear disclosure of material connections and no review suppression. Marketing language tied to enzymatic SVF or culture-expanded ADSCs as a treatment is exposure that no marketing disclaimer can fully cover.
What training should clinicians complete before offering adipose harvest?
Plan on a combination of didactic foundations in biology, pharmacology, and regulation, plus supervised live-patient procedural practice covering tumescent infiltration, harvest technique, processing decisions, and injection technique appropriate to the intended indications. Ask your malpractice carrier, in writing, whether your policy covers the specific procedures you plan to offer, and ask your carrier and any credentialing committee what records they want. They decide what is enough.
Can clinicians legally participate in SVF research?
Yes, within the proper regulatory framework. Conducting SVF research under an FDA-authorized Investigational New Drug application is legal, because the FDA’s IND framework is the legitimate pathway for studying products that the agency considers drugs. What is not legal is offering clinic-prepared enzymatic SVF to patients as a treatment outside of that authorized framework. RMA’s training is focused on clinical service lines clinicians can legally offer today, not on running an IND-authorized trial.
Key takeaways
- The single most important regulatory line in adipose-based regenerative medicine is mechanical versus enzymatic processing. Mechanical processing (MFAT, microfat, nanofat) avoids enzymatic digestion, though homologous use and the device’s cleared indication still apply. Enzymatic processing (SVF) is regulated as a drug.
- FDA regulates enzymatically digested SVF as a drug, and two federal appeals courts (Eleventh Circuit 2021, Ninth Circuit 2024) have ruled for FDA in SVF cases. Clinic-prepared SVF offered as a treatment is not legal in the United States outside of an authorized clinical trial.
- RMA’s adipose training covers mechanical MFAT processing and does not cover SVF preparation or clinical use.
- MFAT produced by a 510(k)-cleared closed-system device is a cleared device for tissue handling, not an approved treatment for any specific indication. Use for named conditions like knee osteoarthritis is off-label.
- Tumescent pharmacology, including delayed lidocaine peaks and CYP3A4 interactions, is central to safe harvesting.
- Match harvest technique to the intended end product: Coleman for structural volumization, microfat for fine aesthetic work, nanofat for skin quality, MFAT for device-based orthopedic applications.
- Evidence differs by use and is not settled for musculoskeletal applications. MFAT for knee osteoarthritis is off-label, and wound care and other cell-based uses are investigational.
- Look for training that covers regulation, pharmacology, technique, and documentation together. Training gives you supervised cases and a method; it does not guarantee a clinical result.
RMA Disclosure
Regenerative Medicine Academy (RMA) is an education company that provides clinician training in some of the techniques discussed in this article. RMA does not provide training on enzymatic SVF preparation or clinical use, because clinic-prepared SVF offered as a treatment is not legal in the United States. This article is educational and does not constitute a claim of clinical superiority, a guarantee of outcomes, or a substitute for individual clinical judgment. Procedures discussed in this article involve off-label use of FDA-cleared devices. The 510(k) clearance for closed-system MFAT devices covers adipose tissue handling in specified surgical applications. Use of MFAT for specific named indications like knee osteoarthritis is off-label unless and until FDA clears that indication. Clinicians may use FDA-cleared devices off-label based on clinical judgment but must obtain informed consent, discuss evidence, risks, and alternatives, and document thoroughly. Scope of practice, supervision requirements, and corporate practice of medicine rules vary by state. Clinicians should consult their state medical board, malpractice carrier, and legal counsel regarding compliance in their jurisdiction before offering adipose-based regenerative procedures.
For clinicians ready to take the next step
Clinicians evaluating an adipose-based service line, or refining an existing one, can explore hands-on procedural curriculum, didactic foundations, and aesthetic-focused programs through RMA’s full course catalog. The catalog covers musculoskeletal, cosmetic, sexual health, and adipose tissue applications, all built around the legal mechanical-processing pathway that U.S. clinicians can actually use in practice today. Ask about dates and fit.
The course that goes with this post
Adipose and MFAT Tissue Harvesting
Donor site selection, the harvest, mechanical MFAT processing and injection technique, with an instructor beside you.
Starting at $5,000 at an instructor’s clinic, or $10,000 inside your practice.
Important information
Education, not medical advice
Regen Med Academy provides education and training for licensed healthcare providers. Everything on this site is for educational purposes only. It is not medical advice, not a treatment recommendation, and not an offer to treat. Providers are responsible for practicing within the scope of their own license and their own state law.
Where a course can run
Courses are taught only in states where the modality is legal for the license you hold. State law in this field changes, sometimes more than once a year. Our reading of each state, with its sources and the date we checked, is on the rules by state page. It is a starting point, not legal advice. It is your responsibility to confirm the modality is legal in your state for your license. Do that before you book. The authority on your own scope is your licensing board, not us. State medical board contact details are published by the Federation of State Medical Boards.
Training on live patients
Procedures performed during training are performed on consenting patients, by licensed providers, under supervision. Participation is voluntary and outcomes vary.
Products and modalities
Some products and modalities discussed in these courses are not FDA approved or cleared for the uses described. Regen Med Academy does not manufacture, sell or endorse any product, and does not approve or clear any product. The FDA publishes guidance for patients and providers on regenerative medicine therapies.
What a certificate is, and is not
Regen Med Academy does not offer CMEs, credit hours or accreditation of any kind. What you receive is a Certificate of Completion. It records that you attended and performed the procedures under supervision. It is not a license, not a board certification, and it does not expand your scope of practice.
Coverage is yours to arrange
You are responsible for your own malpractice coverage. We will help you work out what to ask your carrier, and we recommend getting the answer in writing. Regen Med Academy does not provide, arrange or extend coverage to trainees, and nothing on this page is legal advice or an assurance of coverage.


